Cover Top Placeholder

Spinal Osteoarthritis

Cover Middle Accent
Cover Bottom Height Engine
Last updated:

What is spinal osteoarthritis?

Spinal osteoarthritis is the wear-and-tear arthritis of the spine. Osteoarthritis is the common form of arthritis in which a joint’s smooth cartilage gradually thins and the bone reacts by forming small spurs. In the spine, it affects the facet joints, the small paired joints at the back of each level that guide movement. It is also called spinal arthritis, and, in medical terms, spondylosis, which is the word most often used on scan reports and in referral letters.

It is very common, and largely a normal part of ageing: by later life most people have some osteoarthritic change in the spine, and much of it causes no symptoms at all. For most people it is not serious. It matters when the wear produces a specific problem, such as a nerve compressed by stenosis, facet joint pain that will not settle, or a segment that has become unstable. Spinal osteoarthritis is really an umbrella term for the age-related wear of the spine, and it overlaps closely with several conditions covered in depth elsewhere, facet joint pain, disc degeneration, and the nerve compression that wear can cause. Those are set out further down, and on their own pages.

What does spinal osteoarthritis feel like?

The usual symptoms are back or neck pain and stiffness. The pain is often worst first thing in the morning or after a period of inactivity, eases a little with gentle movement, and tends to be worse from being upright and better lying down. Arthritis in the spine is often mild, and many people have changes on a scan with few or no symptoms. Where bone spurs or thickened joints narrow the space around a nerve, the pain can spread, into the arm from the neck, or into the leg from the lower back, sometimes with numbness or tingling.

Numbness, tingling, or weakness that is spreading or worsening, difficulty walking, or any loss of bladder or bowel control needs prompt assessment.

What causes spinal osteoarthritis?

The main driver is time. As the years pass, the cartilage in the facet joints wears and the body forms spurs in response. Several things influence how early, and how much, this happens:

  • Age: the single biggest factor; osteoarthritic change becomes steadily more common with each decade.
  • Load and previous injury: extra body weight, heavy physical work, or an earlier spine injury all add to the wear.
  • Disc degeneration: as the discs lose height, the facet joints behind them carry more load, which speeds their wear.
  • Genetics: a family tendency to osteoarthritis plays a part.

What are the stages of spinal osteoarthritis?

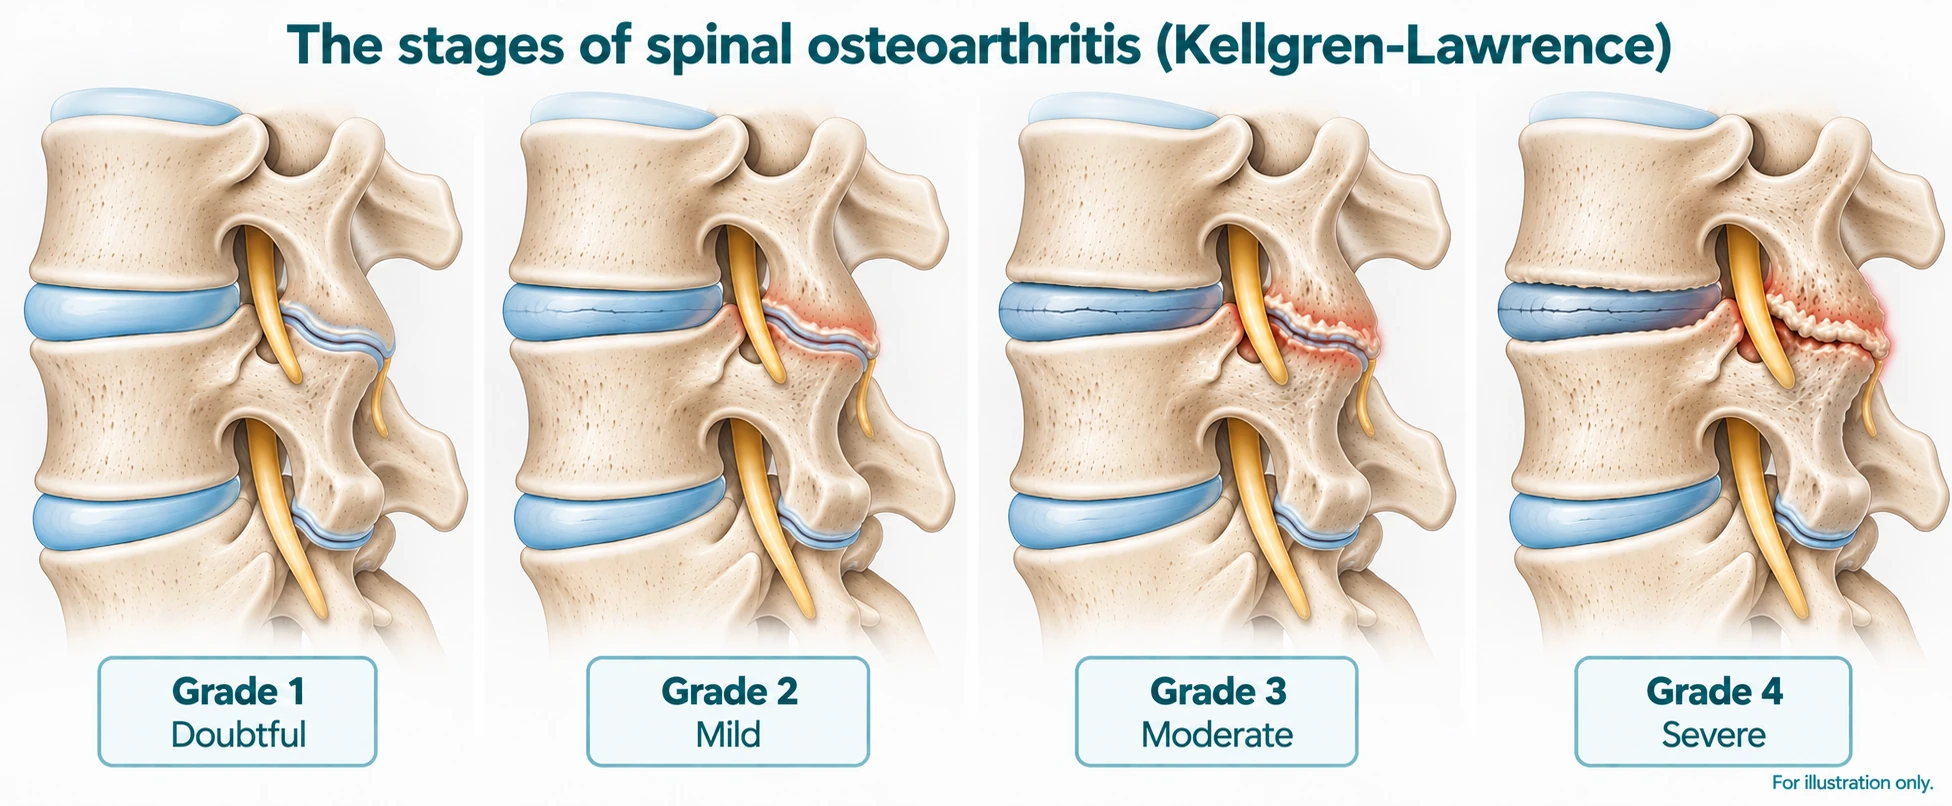
Osteoarthritis is often described in stages, based on how it looks on an X-ray. The most widely used scale, called Kellgren-Lawrence, has four grades and runs from early to advanced:

  • Grade 1, doubtful: the cartilage begins to thin and a small spur may appear at the edge of the joint. Often there are no symptoms.
  • Grade 2, mild: definite spurs at the edges of the joint, with possible narrowing of the joint space.
  • Grade 3, moderate: clear spurs form and the joint space narrows as more cartilage is lost. Stiffness and pain tend to become more consistent.
  • Grade 4, severe: large spurs, marked narrowing, and hardening of the bone; the joints enlarge, and this is the stage where they can crowd nearby nerves and contribute to spinal stenosis.

The most important thing to know about these stages is that the picture on the scan and the pain a person feels often do not match. Studies consistently find that advanced-looking arthritis can be painless, and early arthritis can hurt. Because of that, treatment is guided by symptoms, not by the grade on the X-ray.

How is spinal osteoarthritis diagnosed?

Spinal osteoarthritis is usually diagnosed from the pattern of symptoms and a physical examination, supported by imaging. An X-ray shows the narrowed joints and any spurs; an MRI adds detail about the discs and shows whether a nerve is being compressed. One caution runs through the diagnosis: because these changes are so common with age, finding them on a scan does not by itself prove they are the cause of the pain, which is why the examination and the pattern of symptoms matter as much as the images.

How is spinal osteoarthritis treated?

Most spinal osteoarthritis is managed without surgery, and the mainstays are simple and effective:

  • Exercise and physiotherapy: keeping the spine moving and strengthening the supporting muscles is the most effective long-term measure, and it is the foundation of treatment.
  • Weight and activity: reducing load on the spine, staying active, and pacing aggravating activities all help.
  • Pain relief and injections: anti-inflammatory medication for flare-ups, and, for facet joint pain confirmed by a diagnostic block, a targeted injection or a procedure to calm the small nerve that carries the pain.

Surgery is not a treatment for spinal osteoarthritis in general. It has a role only where the wear has produced a specific, correctable problem, such as a nerve compressed by stenosis, or a segment that has become unstable. Those situations, and the operations for them, are covered on the pages below.

What conditions does spinal osteoarthritis lead to?

Because spinal osteoarthritis is really the wear of the spine over time, it shows up as several more specific conditions, and these are where treatment, including surgery, is actually directed:

  • Facet arthropathy: osteoarthritis of the facet joints themselves, and the direct cause of much arthritic back and neck pain. This is what people usually mean by facet osteoarthritis.
  • Degenerative disc disease: the disc side of the same age-related wear, which often goes hand in hand with facet arthritis.
  • Spinal stenosis: when the spurs and thickened joints of advanced arthritis narrow the space around the spinal nerves, producing leg or arm symptoms.

If you have been told you have spinal osteoarthritis, the more useful question is usually which of these is causing your symptoms, because that is what determines the treatment.

What we see at Spine Connection

Most spinal osteoarthritis needs good conservative care, not surgery, and we are straight with people about that. The cases we treat are the ones where the wear has caused a specific, fixable problem: facet joint pain that has not settled, a nerve pinched by stenosis, or a segment that has become unstable. Where surgery is needed, our German specialists, including Dr. Thomas Bierstedt, favour motion-preserving approaches that relieve the problem without stiffening the whole spine. For earlier facet arthritis, some patients also explore regenerative options such as stem cell therapy, though the evidence for these is still developing.

Frequently Asked Questions

The most widely used scale, Kellgren-Lawrence, runs across four grades. Grade 1 is doubtful, with a possible small bone spur with no joint space narrowing. Grade 2 is mild, with definite spurs and possible narrowing. Grade 3 is moderate, with multiple spurs, definite narrowing and some hardening of the bone. Grade 4 is severe, with large spurs, marked narrowing and clear bone changes. Different centres describe these differently.

For most people it is not serious. It is largely a normal part of ageing. By later life most people have some osteoarthritic change in the spine, and much of it causes no symptoms at all. It becomes significant when it produces a specific problem: a nerve compressed by stenosis, facet joint pain that will not settle, or a segment that has become unstable.

No, and this is the most important thing to understand about the grading. Studies consistently find that advanced-looking arthritis can be completely painless, and early arthritis can hurt considerably. The changes are so common with age that finding them on a scan does not prove they are causing your symptoms. Treatment is guided by how you are affected, not by the grade on the X-ray.

Spondylosis is the medical term for the age-related wear of the spine, and it’s the same thing as spinal osteoarthritis or spinal arthritis. It covers the discs losing height, the facet joints becoming arthritic, and the bone spurs that form in response. It is descriptive rather than a specific diagnosis, which is why the more useful question is usually which part of the wear is causing your symptoms.

Most of it is managed without surgery, and the mainstays are simple. Keeping the spine moving and strengthening the supporting muscles is the most effective long-term measure. Reducing load, staying active and pacing aggravating activities all help. Anti-inflammatory medication helps flare-ups, and for facet joint pain confirmed by a diagnostic block, a targeted injection or procedure can give relief.

Surgery is not a treatment for spinal osteoarthritis in general. It has a role only where the wear has produced a specific, correctable problem, such as a nerve compressed by spinal stenosis, or a segment that has become unstable. If you have been told you have spinal arthritis, the more useful question is which of those, if any, applies to you.

Because it is really the wear of the spine over time, it shows up as several more specific conditions, and those are where treatment is actually directed. Facet arthropathy is osteoarthritis of the facet joints themselves. Degenerative disc disease is the disc side of the same process. Spinal stenosis is what happens when spurs and thickened joints narrow the space around the nerves.

Stuck waiting, or told to live with it?

Spinal osteoarthritis is common, and for most people it is manageable. But if yours has led to a specific problem, facet pain that will not settle, nerve compression, or instability, and you are stuck on a waiting list or have been told simply to live with it, a second opinion is worth having. Our specialists in Germany and Thailand can review your imaging, tell you which part of the wear is actually causing your symptoms, and set out the options, including motion-preserving surgery for the cases that need it, often far sooner than you would be seen at home.

Sources

  1. Osteoarthritis. StatPearls (updated 2023). (Osteoarthritis is cartilage thinning with reactive bone-spur (osteophyte) formation.) (https://www.ncbi.nlm.nih.gov/books/NBK482326/)
  2. Cervical Spondylosis. StatPearls (updated 2025). (Spinal osteoarthritis, or spondylosis, is a natural ageing process affecting the discs, facet joints, and ligaments, present in most people after the fifth decade.) (https://www.ncbi.nlm.nih.gov/books/NBK551557/)
  3. Kohn MD, et al. Classifications in Brief: Kellgren-Lawrence Classification of Osteoarthritis. Clinical Orthopaedics and Related Research, 2016. (The standard radiographic staging of osteoarthritis, from early to advanced.) (https://pubmed.ncbi.nlm.nih.gov/26872913/)
  4. Lumbar Facet Arthropathy. StatPearls (updated 2023). (Osteoarthritis of the facet joints as a cause of back pain.) (https://www.ncbi.nlm.nih.gov/books/NBK538228/)
We're here
to help.
Leave your details and we will contact you to answer your questions.

Get a Spine Specialist's Opinion for Your Spinal Osteoarthritis

Leave your details and we will contact you to answer your questions. We're here to help.


    Join Our Youtube Channel

    Watch videos showcasing the latest technologies and surgery techniques, and keep up to date with patient stories from around the globe.


