Cover Top Placeholder

Kyphosis

Cover Middle Accent
Cover Bottom Height Engine
Last updated:

What is kyphosis?

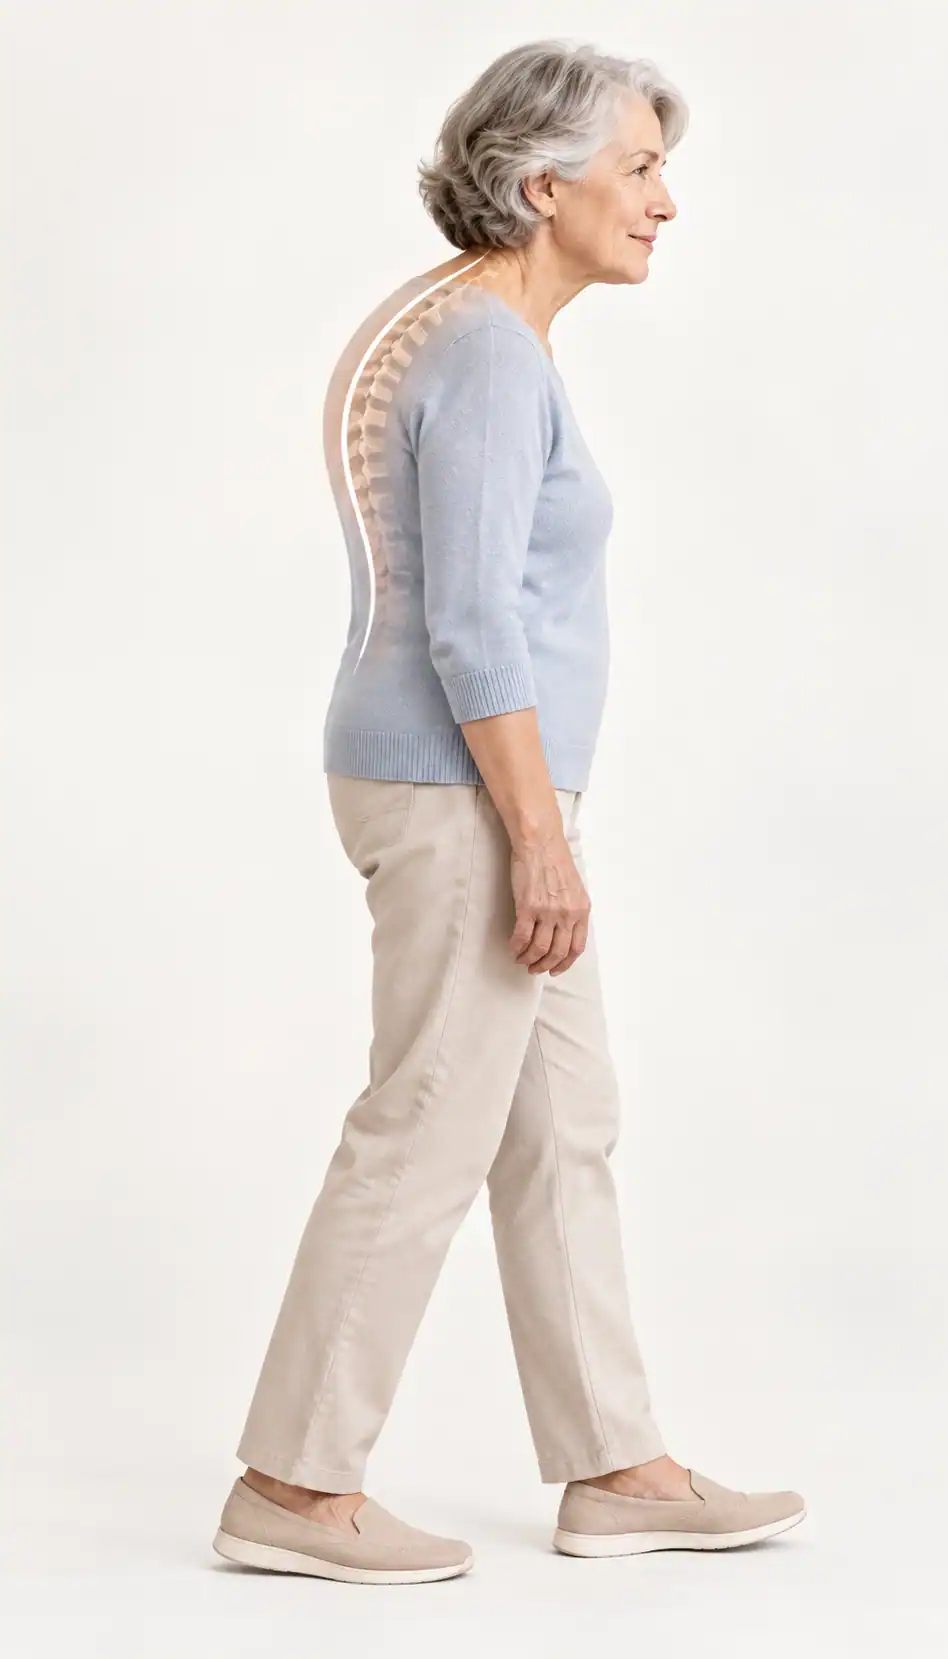
Kyphosis is an excessive forward curve of the spine, most often an exaggerated curve of the middle back that produces a rounded or hunched over posture. Sometimes it’s described as a hunchback or, where it follows collapsed vertebrae in older women, a dowager’s hump. Seen from the side, a healthy spine has gentle curves that alternate to keep the body balanced and upright: the middle back (the thoracic spine) curves forward, a shape called kyphosis, while the neck (the cervical spine) and the lower back (the lumbar spine) gently curve back, a shape called lordosis. Each of these curves is normal in the right amount.

There are two kinds of Kyphosis. Thoracic kyphosis is too much of the forward curve in the middle back. Cervical kyphosis is the opposite problem in the neck: the neck should curve back, but when its discs wear and lose height at the front, that curve flattens or reverses and the head tips forward. Cervical kyphosis is often more treatable, because restoring the lost disc height can rebuild the natural healthy curve.

Most kyphosis is mild and postural, and it improves with physiotherapy and exercise. Some is structural, when the spinal bones or discs have changed shape, so the curve is fixed and does not straighten with effort. This structural kyphosis is the kind that may need treatment. This page explains these kyphosis causes and discusses the different treatment approaches.
Patient Education Video

What does kyphosis feel like?

Most often, kyphosis is a visibly rounded middle back with no pain, and people notice the appearance before any symptom. When it does cause symptoms in the middle back, they are usually pain, stiffness, and muscles that tire from holding the posture. When the neck has lost its normal curve, it can cause neck pain and a head-forward posture, and if worn discs press on nerves it can cause pain, numbness, or weakness into the arms.

Some symptoms need proper medical assessment rather than watching and waiting. These include pain that persists or worsens, a curve that is visibly increasing, difficulty standing upright, or any numbness, tingling, or weakness in the arms or legs. Rapidly worsening weakness or any loss of bladder or bowel control needs urgent care.

Postural or structural kyphosis?

There are important differences between the two.

Postural (flexible) kyphosis: the curve comes from the way the spine is being held, not from a change in its structure. It straightens out when you stand tall or lie flat, and it responds well to physiotherapy, exercises that strengthen the muscles holding you upright, and posture training. This is by far the most common kind, especially in teenagers and younger adults, and it rarely needs anything more.

Structural kyphosis: the curve comes from an actual change in the bones or discs, so it is fixed and does not straighten with effort, because the problem is in the spine itself rather than the muscles around it. This is the kind that may need medical or surgical treatment, and the underlying cause is important.

What causes structural kyphosis?

The common causes of structural kyphosis are:

Worn discs in the cervical spine (neck): when several discs in the neck degenerate and lose height, they lose it mostly at the front, which can flatten or even reverse the neck’s normal inward curve and tip the head forward. This is one of the more treatable structural causes.

Worn discs in the thoracic spine (middle back): similar wear of the discs and facet joints joints lower down can flatten the spine’s natural curves and pull the trunk forward, a common reason for a stooped posture in older adults.

Osteoporotic fractures: when weakened vertebrae collapse into a wedge shape, several of them stacked together produce the forward stoop often seen with osteoporosis.

Scheuermann’s disease: a structural kyphosis that develops during adolescence, where several vertebrae grow into a wedge shape, giving a rigid, sometimes painful curve in the middle back.

After a previous fusion: a spine that was fused without keeping its natural forward and backward curves can be left flat or stooped, sometimes called flatback.

  • Gibbus deformity: where one or more vertebral bodies collapse at the front, the result is a sharp, angular hump rather than the smooth rounded curve of ordinary kyphosis, and it becomes more obvious on bending forward. Worldwide the most common cause is spinal tuberculosis, known as Pott’s disease. Other causes include spinal infection, significant trauma, and congenital abnormality. Where infection is the cause, the infection itself is treated first, and by an infection specialist, rather than by spinal surgery alone.

How is kyphosis graded?

In the middle back, kyphosis is measured with a standing side-on X-ray as the Cobb angle.

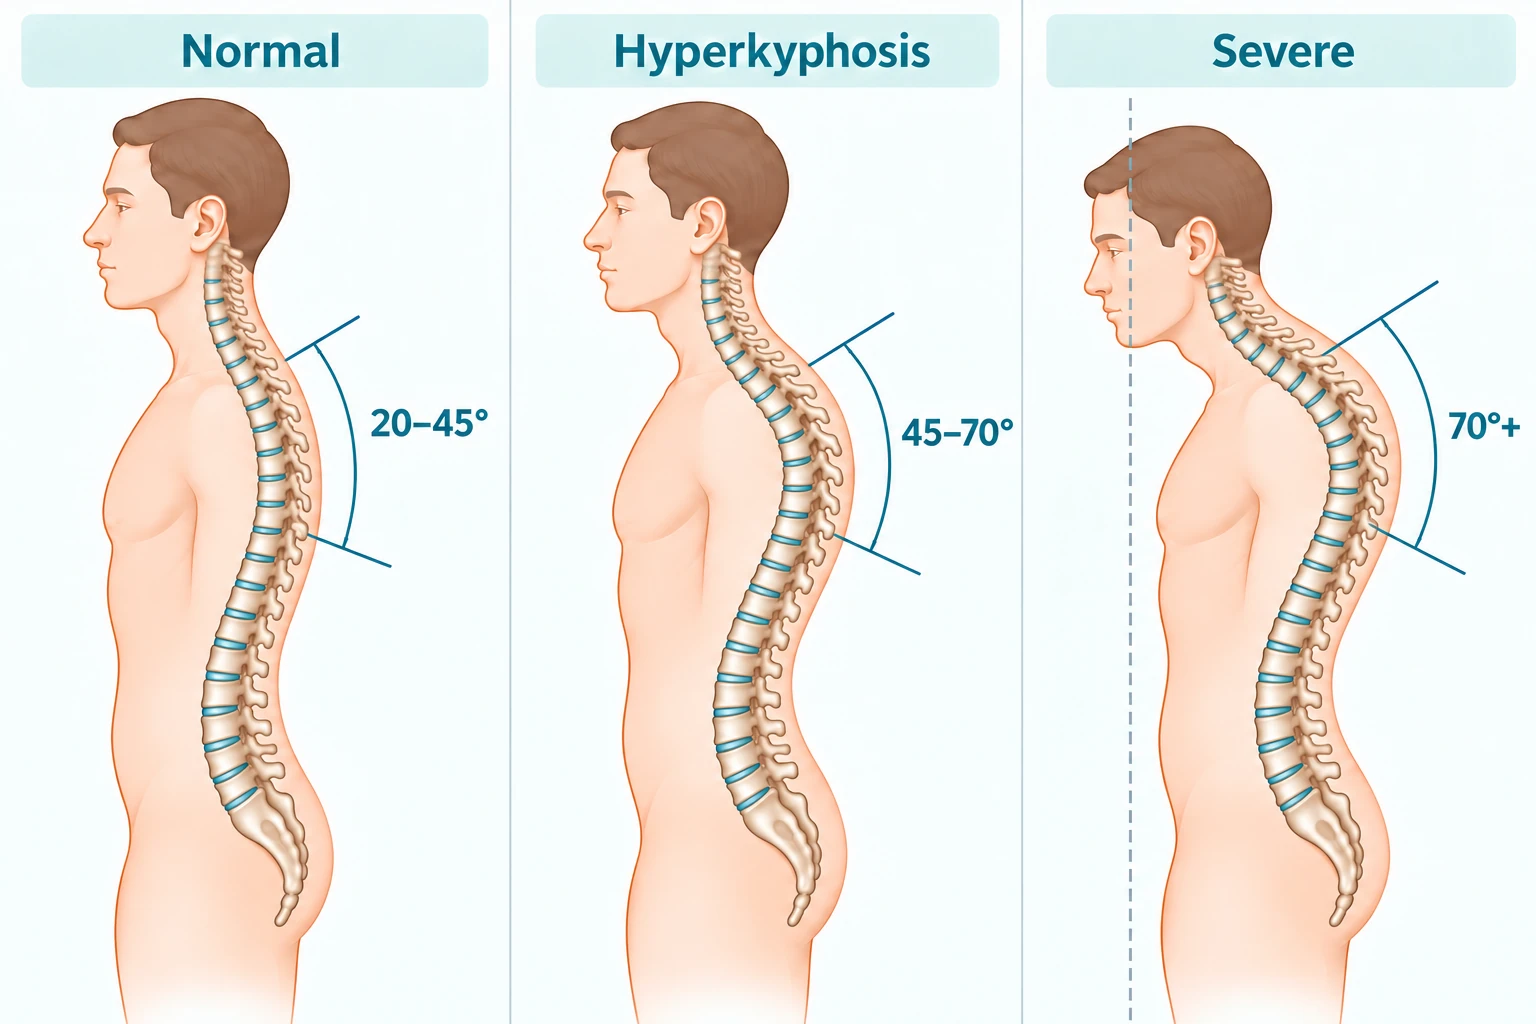
Normal: a forward curve in the middle back of roughly 20 to 45 degrees is normal.

Hyperkyphosis: a curve beyond about 45 to 50 degrees is more than expected.

Severe: larger curves, often beyond about 70 to 75 degrees, are more likely to be rigid, painful, or progressive, and are more likely to be considered for surgery.

Along with the Cobb angle, a patient’s clinical symptoms are also important when it comes to recommending surgery. The neck is judged differently, where any any loss of the normal inward curve is abnormal.

How is kyphosis treated?

Treatment follows directly from whether the curve is postural or structural, and from its cause.

Postural and mild curves: these are managed without surgery: physiotherapy, exercises to strengthen the muscles that hold the spine upright, and posture training. This is the large majority of cases.

Structural curves: where the curve is fixed and causes pain, nerve symptoms, or a posture that affects daily life, treatment targets the cause. Conservative care and pain relief come first. Where a correctable structural cause is driving the curve, surgery to treat it and restore alignment is considered.

What are the surgery options for kyphosis?

Surgery is matched to the cause of the kyphosis

Worn discs in the neck: the goal is to rebuild the height the discs have lost. Our surgeons perform cervical disc replacement at one to four levels where indicated, replacing each worn disc with a motion-preserving implant. Restoring the disc height at the front rebuilds the neck’s inward curve, and because the implants keep the segments moving rather than fusing them, the neck keeps its movement. With rehabilitation afterwards, cervical disc replacement has been shown to improve the neck’s lordosis.

Scheuermann’s or advanced thoracic kyphosis: a large, rigid curve in the middle back can be corrected and held with instrumentation, rods and screws that realign the spine and fuse the corrected curve. This is reserved for severe or progressing curves, or ones causing significant pain.

Osteoporotic fractures, or flatback after a fusion: here surgery stabilises the collapsed vertebrae, or realigns a spine that was left flat, to restore an upright posture.

Most kyphosis never needs surgery. When it does, the aim is to treat the cause and restore alignment, preserving movement where possible.

What we see at Spine Connection

Most kyphosis we are asked about is postural, and the honest answer is that it belongs with a physiotherapist. The cases we treat are structural: a fixed curve driven by a change in the spine. In the neck in particular, worn discs that have flattened the natural curve are a problem we treat often, with motion-preserving disc replacement at up to four levels where needed, restoring both the curve and comfort.

Dr. Bernd Illerhaus is a neurosurgeon at ONZ International in Germany, one of the world’s leading centres for cervical artificial disc replacement. His particular focus is motion-preserving disc replacement in the cervical and lumbar spine, he performs around 400 spine operations a year, and he is an international reference surgeon and co-developer of disc-replacement implants who teaches other European surgeons.

Frequently Asked Questions

A gibbus is a specific form of kyphosis with a sharp, angular hump rather than the smooth rounded curve of ordinary kyphosis. It happens when one or more vertebral bodies collapse at the front, creating an abrupt angle at that point. It becomes more obvious when bending forward. The most common cause worldwide is spinal tuberculosis, known as Pott’s disease; other causes include spinal infection, trauma, and congenital abnormality.

The rounded upper back most people mean by “hunchback” is kyphosis, and the most common form is postural i.e. The curve comes from how the spine is being held rather than a change in its structure, and it straightens when you stand tall. Structural causes include collapsed vertebrae from osteoporosis, worn discs, Scheuermann’s disease in adolescence, and a spine left flat or stooped after a previous fusion.

Postural kyphosis usually improves substantially with physiotherapy, strengthening the muscles that hold the spine upright, and posture training, as there is no structural change to undo. Structural kyphosis does not straighten with effort, since the shape of the bones or discs has changed. There, treatment targets the cause, and in some cases surgery can restore alignment.

In the middle back, a forward curve of roughly 20 to 45 degrees is normal, measured as the Cobb angle on a standing side-on X-ray. Beyond about 45 to 50 degrees is more than expected. Curves beyond about 70 to 75 degrees are more likely to be rigid, painful or progressive and are the ones most often considered for surgery. The neck is judged differently, where any loss of the normal inward curve is abnormal.

Postural kyphosis straightens out when you stand tall or lie flat, because it comes from muscle balance and habit rather than the shape of the spine. It responds well to exercise and posture work and is by far the most common kind. Structural kyphosis does not straighten with effort, because the bones or discs have changed shape. That distinction decides everything about how it is treated.

Often, yes, and it is one of the more treatable structural causes. The neck should curve inward; when several discs wear and lose height at the front, that curve flattens or reverses and the head tips forward. Rebuilding the lost disc height can restore the curve, and motion-preserving disc replacement does this while keeping the segments moving rather than fusing them.

It can. Age-related kyphosis is driven by several things together, such as discs losing height, vertebrae collapsing where bone has weakened with osteoporosis, and weakening of the muscles that hold the spine upright. That is why a curve that is visibly increasing, rather than one that has been stable for years, is worth having assessed, particularly if bone health has not been checked.

Been told your posture is a problem?

If your rounded posture or forward-tipped neck comes with pain, is getting worse, or has been linked to worn discs, collapsed vertebrae, or a previous fusion, it is worth a proper look. Our specialists in Germany and Thailand can review your imaging and tell you whether it is postural and best handled with therapy, or structural and treatable, and if so, how. Where the cause is worn discs in the neck, a motion-preserving disc replacement can restore the curve.

Sources

  1. Kyphosis. StatPearls (updated 2023). (A normal forward curve becomes hyperkyphosis when excessive; anterior wedging of the vertebrae increases the angle; age-related kyphosis is multifactorial, including disc degeneration, osteoporotic compression fractures, and muscle weakness.) (https://www.ncbi.nlm.nih.gov/sites/books/n/statpearls/article-23963/)
  2. Scheuermann Disease. StatPearls (updated 2023). (A structural adolescent kyphosis defined by anterior wedging of at least 5 degrees across 3 or more adjacent vertebrae.) (https://www.ncbi.nlm.nih.gov/books/NBK499966/)
  3. Restoring cervical sagittal alignment by cervical disc arthroplasty: a prospective study. 2023. (Cervical disc replacement increased the C2 to C7 curve after surgery, restoring cervical sagittal balance, including in more degenerated spines.) (https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10668056/)
  4. Adult Spinal Deformity: A Comprehensive Review of Current Advances. Asian Spine Journal, 2022. (Age-related degeneration and loss of sagittal balance drive deformity and symptoms; treatment is guided by symptoms and balance rather than the curve alone.) (https://www.asianspinejournal.org/journal/view.php?doi=10.31616/asj.2022.0376)
We're here
to help.
Leave your details and we will contact you to answer your questions.

Get a Spine Specialist's Opinion for Your Kyphosis

Leave your details and we will contact you to answer your questions. We're here to help.


Join Our Youtube Channel

Watch videos showcasing the latest technologies and surgery techniques, and keep up to date with patient stories from around the globe.


