Cover Top Placeholder

Scoliosis

Cover Middle Accent
Cover Bottom Height Engine
Last updated:

What is scoliosis?

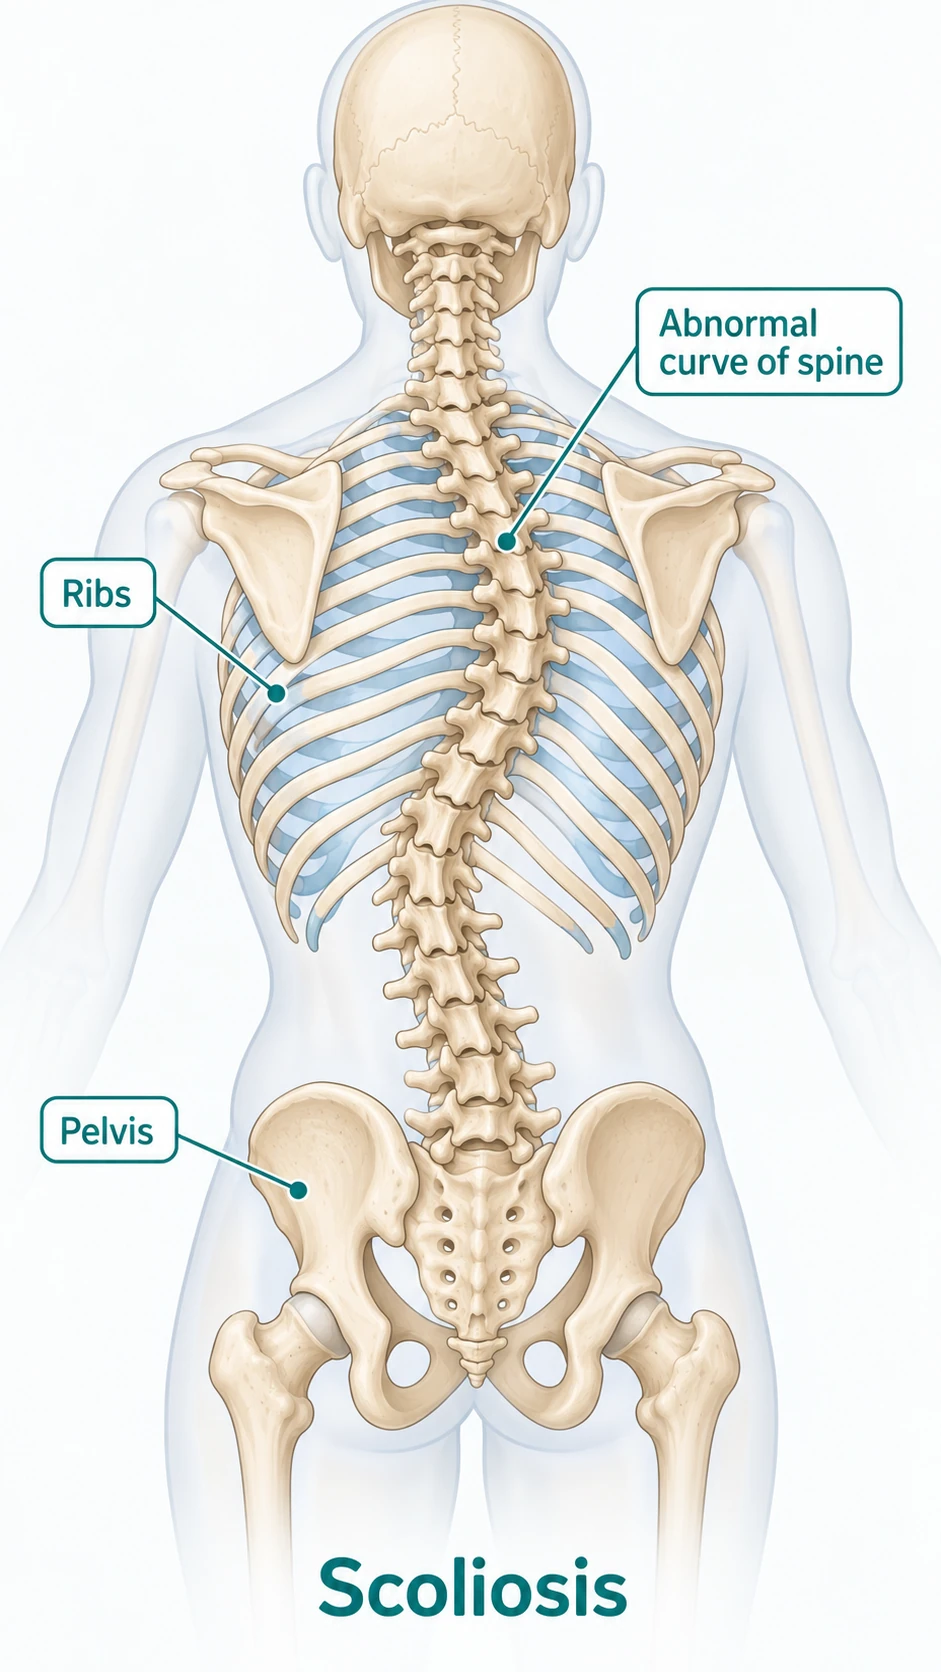
Scoliosis is a sideways curve of the spine, often described simply as curvature of the spine. Seen from behind, a spine with scoliosis looks more like an S or a C than a straight line, and the curve is usually accompanied by some rotation. It is common, and most curves are mild, cause no symptoms, and never need treatment. What matters is the size of the curve, whether it is getting worse, whether it is causing pain or pressing on nerves (most often in adults), and, with a large curve in the chest, whether it is starting to affect the lungs and breathing.

If scoliosis treatment is needed, it will depend on what type of scoliosis it is. A curve in a growing child raises different questions compared to a curve that develops later in life through spinal wear and degeneration. The sections below help explain the difference.
Patient Education Video

What does scoliosis feel like?

In children and teenagers, scoliosis is usually painless, and it is often noticed by its appearance rather than by any symptom: uneven shoulders, one shoulder blade more prominent than the other, an uneven waistline, a hip that sits higher, or a rib hump that shows when bending forward. Because it rarely hurts at this stage, it can go unnoticed until a growth spurt makes the curve more obvious.

In adults, scoliosis is more likely to cause symptoms. The curve and the underlying spinal degeneration behind it can narrow the space around the nerves. This can cause back pain, stiffness, and leg pain, numbness, or heaviness on walking, much like spinal stenosis. Larger curves can also affect posture and balance.

Some symptoms need urgent attention rather than watchful waiting. This includes worsening weakness in a leg, a foot that begins to drag, or any loss of bladder or bowel control.

What causes scoliosis?

Scoliosis is grouped by its cause, and the two that matter most in practice are the first two below:

  • Idiopathic (no known cause): by far the most common, making up around 80% of cases. It has no single identifiable cause and usually appears during childhood growth, most often as adolescent idiopathic scoliosis, which is more common in girls and is generally painless. This is worth stating plainly, because people often ask what they did to cause it: idiopathic scoliosis is not caused by posture, by carrying a heavy bag, or by sleeping position, despite how often those are blamed.
  • Degenerative (adult): develops later in life as the discs and facet joints wear unevenly and let the spine curve. This is the type most likely to cause back and leg pain.
  • Congenital: present from birth, when the vertebrae do not form properly in the womb.
  • Neuromuscular: caused by a condition affecting the nerves or muscles that support the spine, such as cerebral palsy, muscular dystrophy, or spina bifida.

How is scoliosis diagnosed?

Scoliosis is often first picked up on a physical examination, including the forward-bend test, where the curve and any rib hump become easier to see. A standing full-length X-ray of the spine then confirms it and measures the curve as the Cobb angle, which is explained in the next section. An MRI or CT scan may be added to plan surgery or to look for an underlying cause, particularly in very young children or with unusual curves.

How is scoliosis graded?

Scoliosis is measured on a standing X-ray as the Cobb angle, the angle of the curve. A curve of 10 degrees or more counts as scoliosis, and the size of the angle determines what treatment what, if any, is required.

Mild (10 to 25 degrees): often causes no symptoms and, especially once growth has finished, may simply be monitored.

Moderate (25 to 45 degrees): more noticeable, and in a child who is still growing this is the range where a brace is usually considered to stop it worsening.

Severe (more than 45 to 50 degrees): more likely to progress and to cause symptoms or visible imbalance, and the range where surgery is usually discussed. A very large curve in the chest can also begin to restrict the lungs and breathing.

As with other spine conditions, the angle guides treatment decisions but does not tell the whole story, particularly in adults, where the clinical symptoms such as any pain or nerve issues are more important.

How is scoliosis treated?

Most scoliosis is mild and needs nothing more than occasional monitoring. What is done beyond that depends on age, the size of the curve, and whether it is still getting worse.

1. Monitoring: small curves, especially in a growing child, are watched with periodic X-rays to see whether they progress. Many never do.

2. Bracing (growing children): for a moderate curve in a child who is still growing, studies show a brace can stop the curve worsening. A brace holds the curve rather than straightening it, and it is not used to correct curves in adults.

3. Scoliosis-specific physiotherapy: structured exercise approaches such as the Schroth method can support bracing and posture in growing children.

4. Surgery: considered for a large or progressing curve, in children usually beyond about 45 to 50 degrees, where a very large curve is affecting breathing, or, in adults, where the curve causes significant pain, nerve compression, or imbalance that has not settled with conservative care.

What are the surgery options for scoliosis?

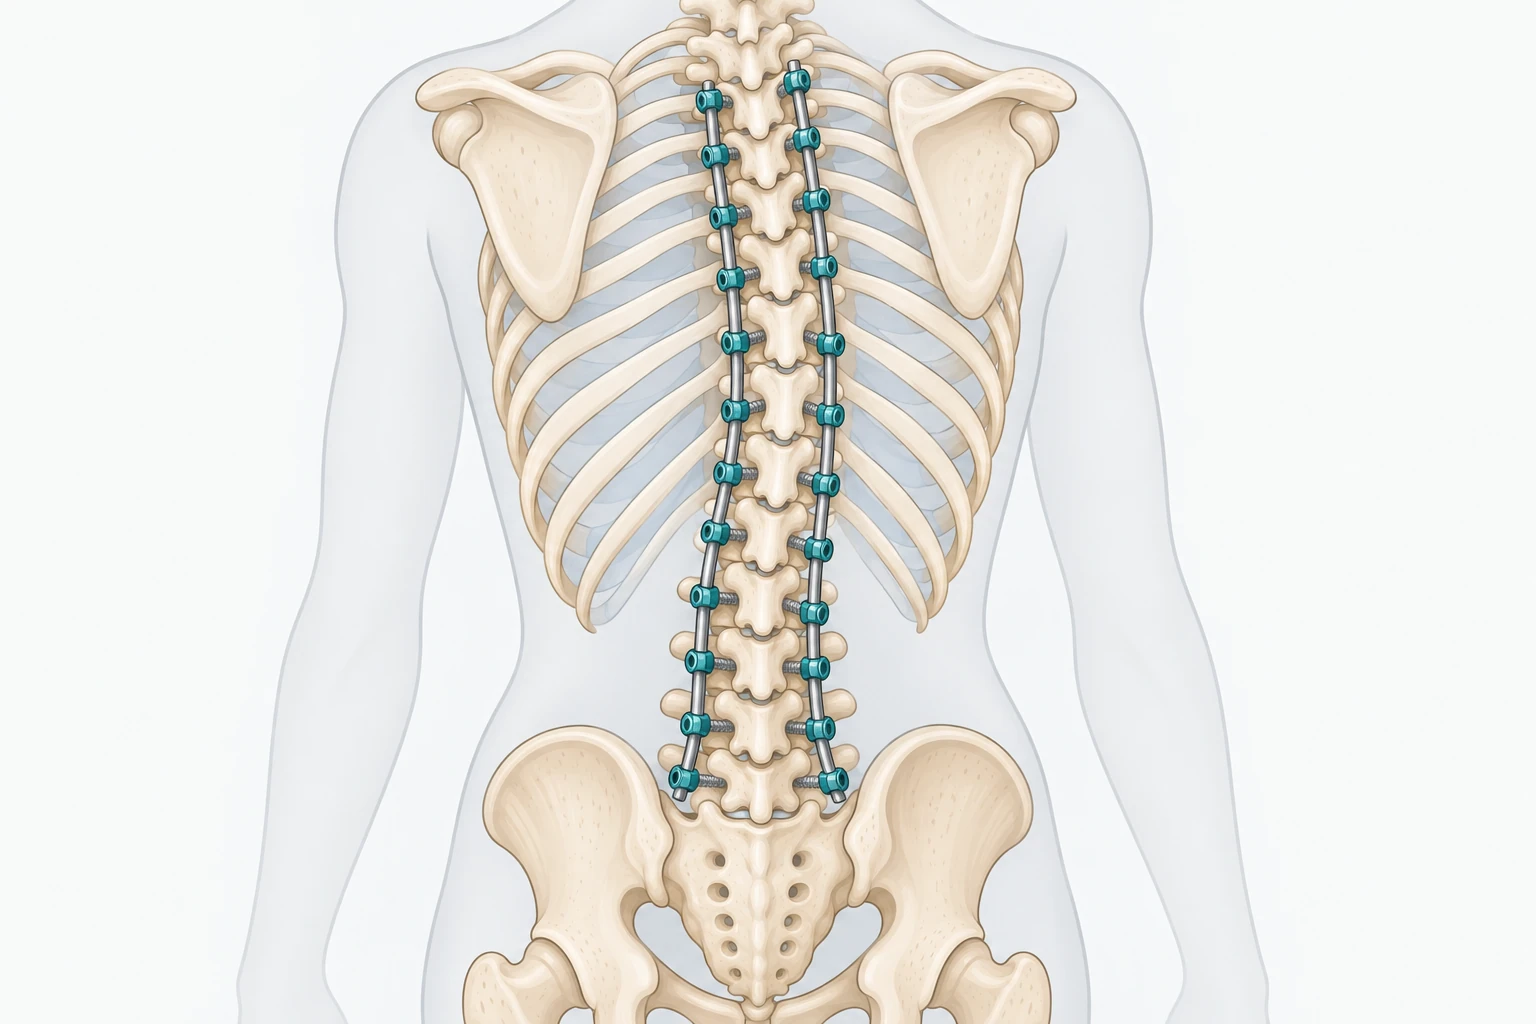
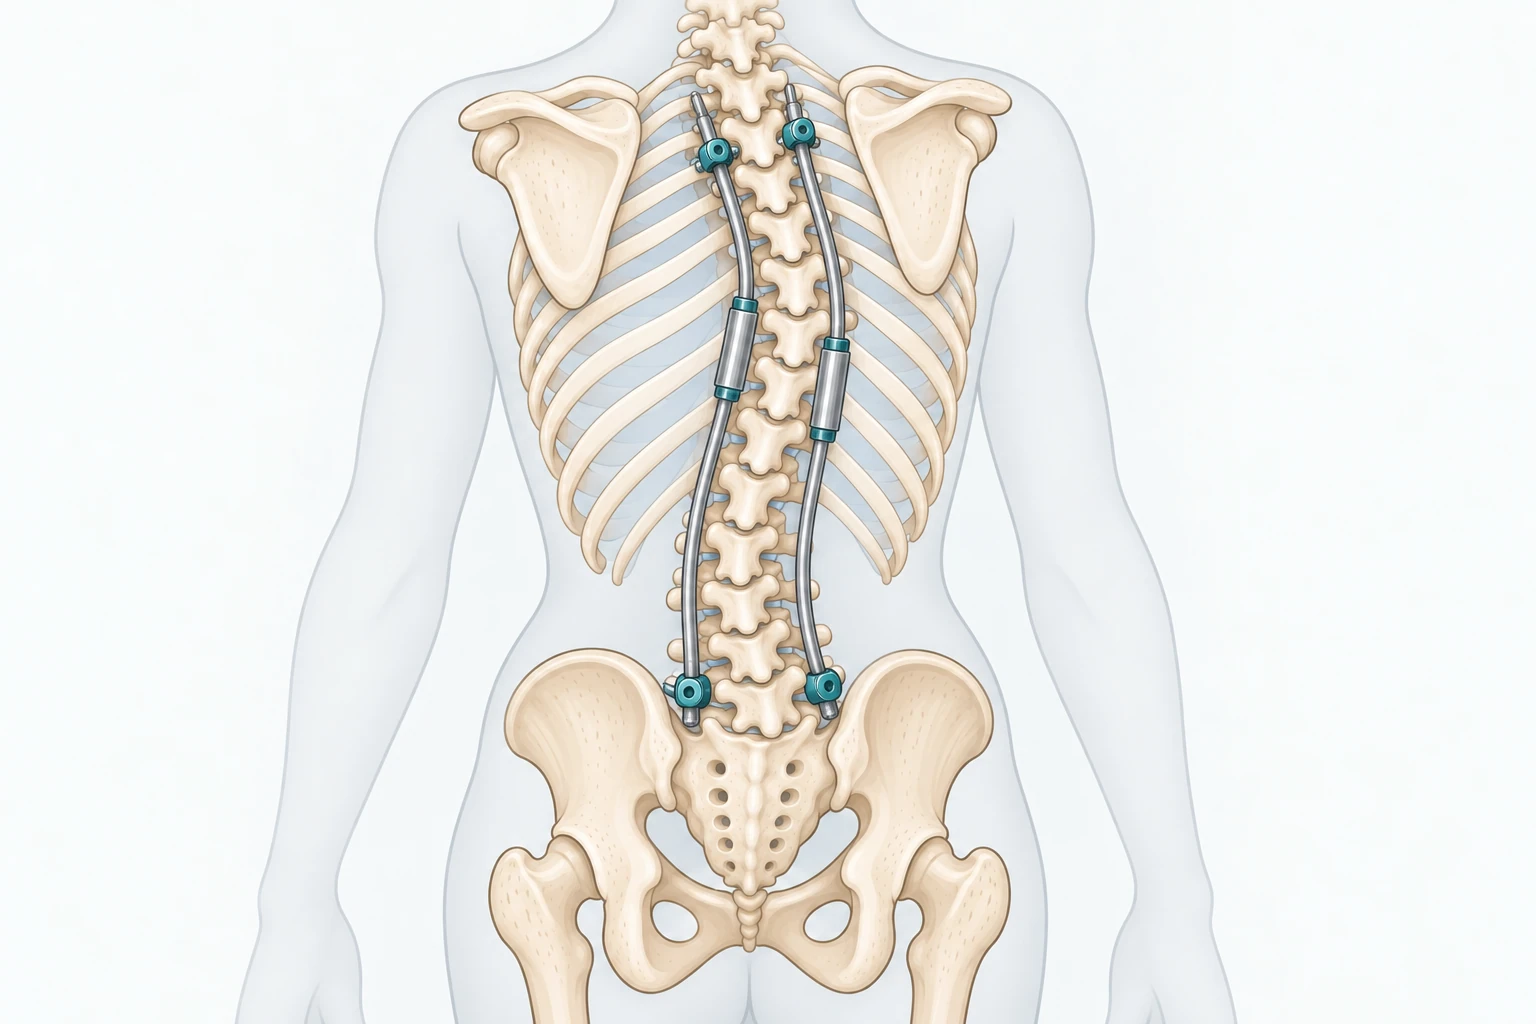
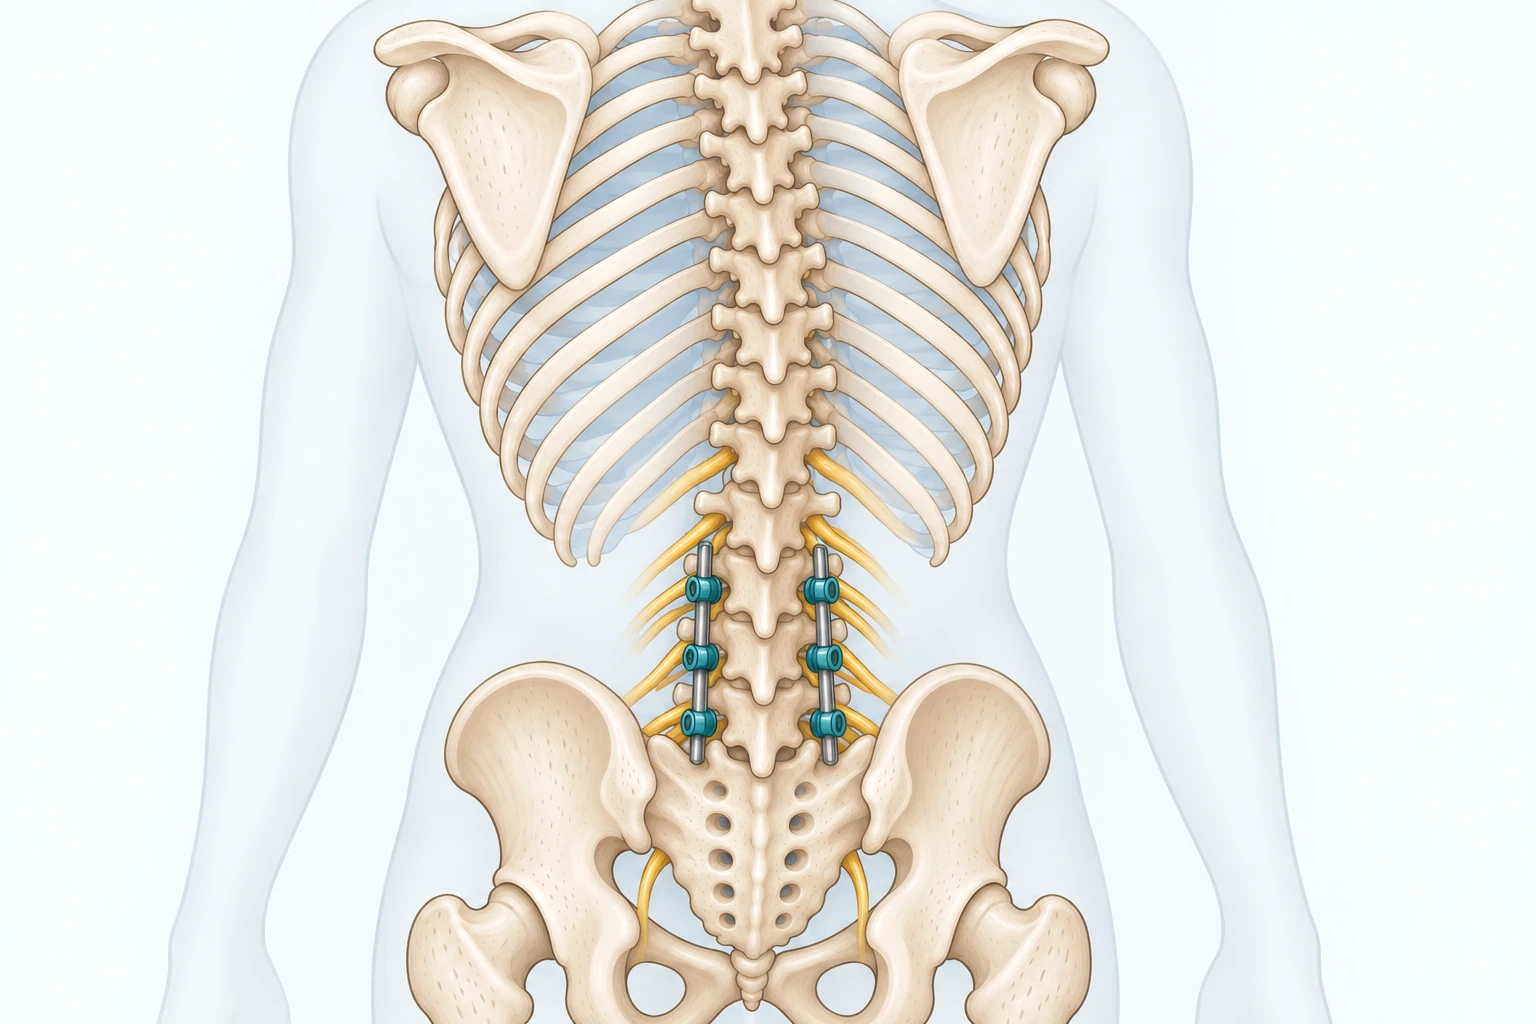
The right operation depends above all on age, and on whether the problem is the curve itself or the symptoms it causes. The below 3 images are for illustration only.

1. Correction and fusion

For a large or progressing curve, most often in adolescents, the spine is realigned with rods and screws and the corrected segment is fused so it holds. In carefully selected younger patients, a newer motion-preserving technique called vertebral body tethering can guide a curve straighter as the child grows without fusing the spine, though it is still being studied.

2. Growing-rod systems (young children)

Fusing the spine of a child who is still growing would stunt that growth, so expandable growing rods are used instead. Modern magnetically controlled rods can be lengthened from outside the body as the child grows, which avoids repeated operations.

3. Decompression, with correction where needed (adult degenerative scoliosis)

In adults the problem is usually the pain and nerve compression the curve causes rather than its appearance. Studies suggest that for some adults whose main problem is leg pain, freeing the trapped nerves (decompression) can be enough on its own, while a curve that is unstable or is driving the symptoms may need realignment and fusion, often through minimally invasive, muscle-sparing approaches. The goal is a balanced, comfortable spine, not a perfectly straight X-ray.

Most scoliosis never needs surgery. When it does, the aim is to match the operation to the person’s age, curve, and symptoms rather than to fit everyone to the same procedure.

What we see at Spine Connection

Scoliosis is one condition where the right answer varies enormously with age. A child’s curve is about growth and progression, while an adult’s is usually about pain, nerve compression, and balance. It’s important to get that distinction right, and not over-treat a curve that is stable and painless.

Dr. Athikom Methathien is a scoliosis and spinal deformity surgeon at Bangkok International Hospital, and an Elite Active International member of the Scoliosis Research Society. He completed dedicated scoliosis and deformity fellowships in Germany, under Professor Henry Halm at the Scoliosis Zentrum in Neustadt, and in the United States at the Rothman Institute in Philadelphia. He treats both children and adults, including the use of magnetically controlled growing rods for children who are still growing, and over his career he has performed more than 3,000 spine operations.

Frequently Asked Questions

In about 80 percent of cases, idiopathic scoliosis can happen without cause, and it usually appears during childhood growth. Other forms have clear causes: degenerative scoliosis develops later in life as the discs and facet joints wear unevenly; congenital scoliosis is present from birth where the vertebrae did not form properly; and neuromuscular scoliosis is caused by a condition affecting the nerves or muscles supporting the spine.

For the most common form, you do not get it from anything you did. It is not caused by poor posture, carrying a heavy bag, or sleeping position, despite how often those are blamed. Adolescent idiopathic scoliosis develops during growth for reasons that are not fully understood, and it is more common in girls. Adult degenerative scoliosis is different and develops from uneven wear over time.

It is the measurement of the curve on a standing full-length X-ray, and it guides what needs doing. A curve of 10 degrees or more counts as scoliosis. Mild is 10 to 25 degrees and is often just monitored. Moderate is 25 to 45 degrees, and in a child still growing this is where a brace is usually considered. Severe is beyond 45 to 50 degrees, and the range where surgery is discussed.

In children and teenagers scoliosis is typically painless and noticed by appearance rather than symptoms: uneven shoulders, one shoulder blade more prominent, an uneven waistline, a hip sitting higher, or a rib hump that shows on bending forward. In adults it is more likely to cause symptoms, including back pain, stiffness, and leg pain or heaviness on walking as the space around the nerves narrows.

Many curves never progress. In a growing child, the risk of progression is highest during growth spurts, which is why periodic monitoring matters at that stage. Once growth has finished, a mild curve often stays stable. In adults, degenerative scoliosis can slowly increase as the spine wears, and there the concern is usually pain, nerve compression and balance rather than the size of the curve itself.

No. Most scoliosis is mild and needs nothing more than occasional monitoring. For a moderate curve in a child who is still growing, a brace can stop it worsening. Surgery is considered for a large or progressing curve, usually beyond about 45 to 50 degrees in children, where a very large curve is affecting breathing, or in adults where the curve causes significant pain, nerve compression or imbalance.

Yes. Adult degenerative scoliosis develops later in life as the discs and facet joints wear unevenly and allow the spine to curve. It is a different problem from the childhood form: the concern is usually the pain and nerve compression the curve causes rather than its appearance, and treatment is aimed at symptoms and balance. For some adults whose main problem is leg pain, freeing the trapped nerves can be enough on its own.

Been told you or your child needs scoliosis surgery?

If you or your child has been diagnosed with scoliosis, or told an operation is needed, it is worth a second opinion from a surgeon who treats curves like this every week. Our scoliosis specialist in Thailand, alongside our German centre, can review the imaging and tell you honestly whether the curve simply needs watching, whether bracing or therapy fits, or whether surgery is the right step, and if it is, what kind.

Sources

  1. Adolescent Idiopathic Scoliosis. StatPearls (updated 2023). (The most common form of scoliosis; idiopathic means no congenital, syndromic, or neuromuscular cause; diagnosis and grading by Cobb angle.) (https://www.ncbi.nlm.nih.gov/books/NBK499908/)
  2. Current concepts in the diagnosis and management of adolescent idiopathic scoliosis. 2020. (Diagnosis and classification by Cobb angle; bracing effective when worn consistently; surgery generally considered for curves beyond 40 degrees; vertebral body tethering as a motion-preserving option.) (https://pmc.ncbi.nlm.nih.gov/articles/PMC7250959/)
  3. Adult Spinal Deformity: A Comprehensive Review of Current Advances. Asian Spine Journal, 2022. (Age-related degeneration and sagittal imbalance drive back pain, neurological symptoms, and deformity; treatment is guided by symptoms and balance.) (https://www.asianspinejournal.org/journal/view.php?doi=10.31616/asj.2022.0376)
  4. Echt M, et al. Decompression Alone in the Setting of Adult Degenerative Lumbar Scoliosis and Stenosis: A Systematic Review and Meta-Analysis. Global Spine Journal, 2023. (Decompression alone can help selected patients with nerve-related leg pain, while an unstable or symptom-driving curve may need fusion.) (https://journals.sagepub.com/doi/10.1177/21925682221127955)
We're here
to help.
Leave your details and we will contact you to answer your questions.

Get a Spine Specialist's Opinion for Your Scoliosis

Leave your details and we will contact you to answer your questions. We're here to help.

    Join Our Youtube Channel

    Watch videos showcasing the latest technologies and surgery techniques, and keep up to date with patient stories from around the globe.