Cover Top Placeholder

Spondylolisthesis

Cover Middle Accent
Cover Bottom Height Engine
Last updated:

What is spondylolisthesis?

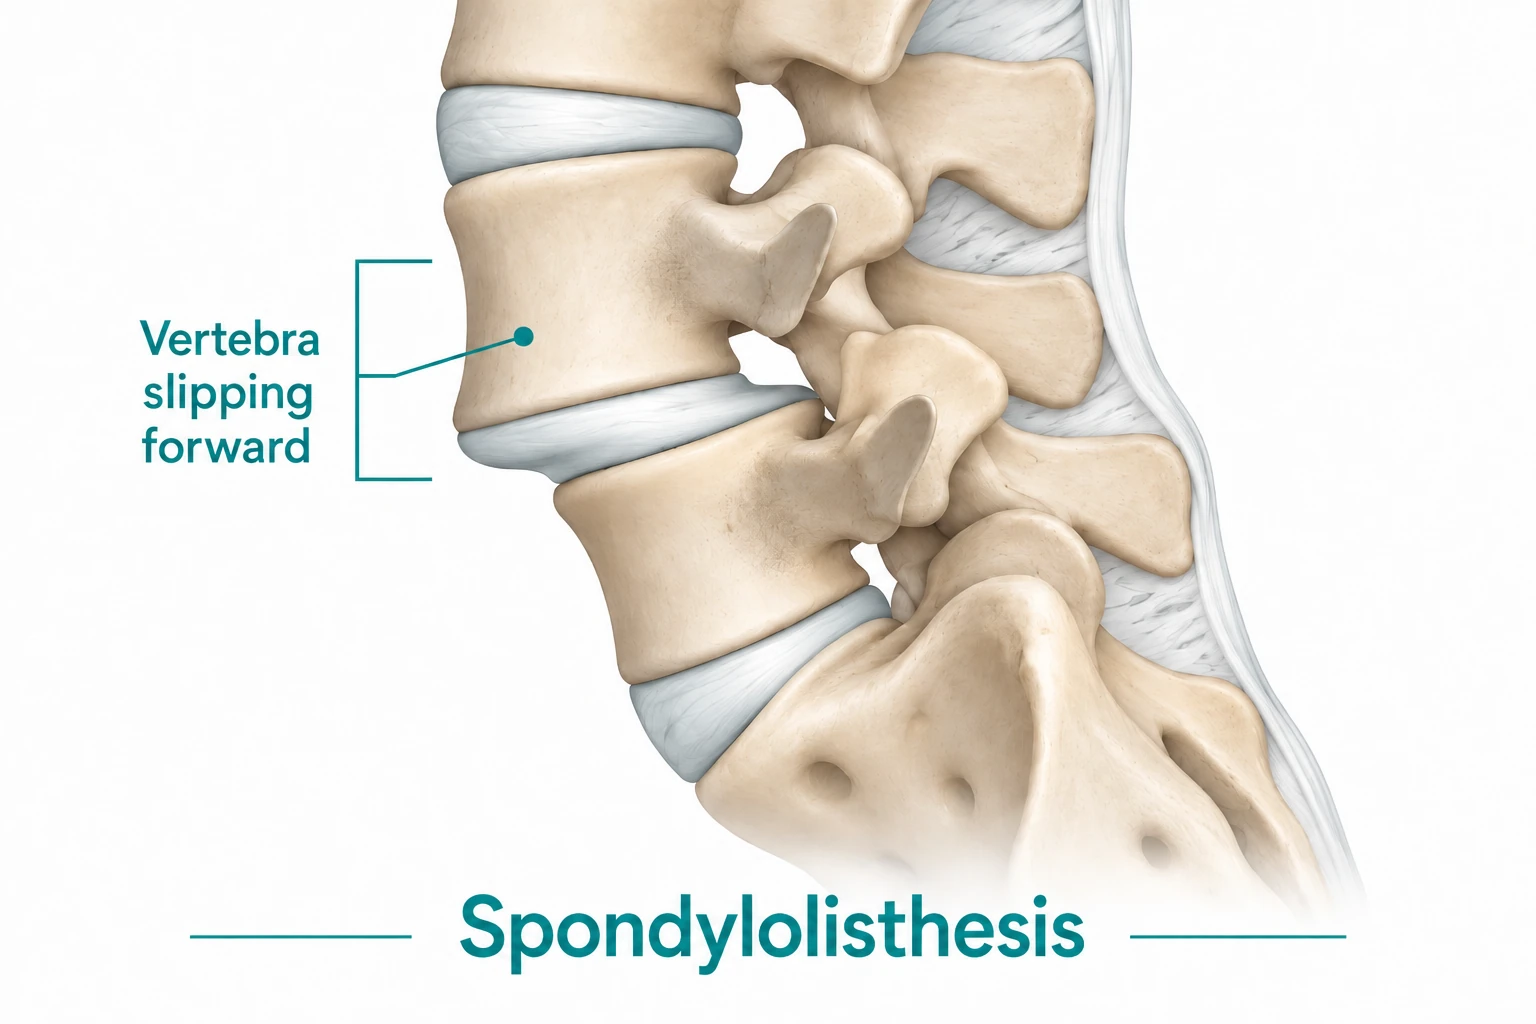
Spondylolisthesis is when one vertebra slips forward over the one below it. It happens most often in the lower back. When a vertebra slips backwards instead, the same problem is called retrolisthesis. On a scan report you may simply see listhesis, meaning a vertebra out of line with the one below, or anterolisthesis for a forward slip. The slip itself is only part of the picture: what matters is what caused it, how far it has moved, whether it is stable, and whether it is pressing on any nerves.

Many people have a slip and no symptoms at all, and the size of the slip does not reliably predict how much pain it causes. A small slip can be painful and a larger one can be silent, which is why the scan is always read alongside how a person actually feels.
Patient Education Video

What does spondylolisthesis feel like?

The most common symptom is lower back pain, often worse with standing, walking, or bending backwards, and easier with rest. Positions and activities that arch the lower back tend to aggravate it, including standing for long periods and walking downhill, while sitting and forward-leaning positions usually give relief. Tight hamstrings are common. If the slip narrows the space around the nerves, it can also cause pain, numbness, tingling, or weakness that travels into the buttock and leg, and in older adults it can produce the leg heaviness on walking that comes with spinal stenosis.

Some symptoms need urgent medical attention rather than watchful waiting: loss of bladder or bowel control, numbness around the groin or inner thighs, or leg weakness that is quickly getting worse. These can signal serious nerve compression and are a medical emergency.

What causes spondylolisthesis?

There are a few different causes, and the two that matter most in practice are:

  • Isthmic spondylolisthesis. A small stress fracture or defect in a part of the vertebra called the pars interarticularis lets it slip. It often starts in youth, particularly in sports that repeatedly arch the lower back such as gymnastics, cricket, or weightlifting, and may not cause symptoms until adulthood.
  • Degenerative spondylolisthesis. Age-related wear of the discs and facet joints loosens the segment and lets a vertebra drift forward, most often at L4/L5. It is more common with age and in women, and the slip is usually low-grade.

Less common causes include a slip present from birth (congenital or dysplastic), a slip from a fracture (traumatic), and one caused by disease weakening the bone (pathological). Because spondylolisthesis so often sits alongside wear in the discs, joints, and canal, it frequently travels with other conditions.

How is spondylolisthesis diagnosed?

A standing side-on X-ray shows the slip and is used to grade it on the Meyerding scale, which is set out in the section that follows.

X-rays taken bending forwards and backwards show whether the segment moves abnormally, which is what tells the surgeon if the slip is stable or unstable. An MRI or CT scan then shows whether the slip is pressing on nerves and gives the detail of the bone and discs. As always, the imaging is interpreted alongside the symptoms.

What are the grades of spondylolisthesis?

A slip is measured on a standing side-on X-ray using the Meyerding scale, which grades it by how far one vertebra has slipped over the one below, expressed as a percentage.

Grade I: up to 25% of the way forward. This is the most common, and most degenerative slips stay here.
Grade II: 25 to 50%.
Grade III: 50 to 75%.
Grade IV: 75 to 100%. A vertebra that has slipped right off the one below, beyond 100%, is called spondyloptosis.

The grade guides treatment: low-grade slips (Grade I and II) are usually stable and often managed without surgery, while higher grades are more likely to need stabilising. It does not, by itself, predict pain, a Grade I slip can be painful and a higher one can cause few symptoms, so how you are affected matters as much as the number.

How is spondylolisthesis treated?

Most spondylolisthesis, especially a stable, low-grade slip, is managed without surgery.

1. Conservative care (first line). Guidelines recommend starting here: staying active, physiotherapy and core strengthening, activity modification to avoid the movements that aggravate it, and pain relief where appropriate. Injections can help settle a flare or calm an irritated nerve. Many people need nothing more.

2. Surgery. Surgery is considered when symptoms persist despite conservative care, when a slip is unstable or progressing, or when it is compressing nerves and causing leg symptoms or weakness. The aim is to take the pressure off the nerves and to stabilise the segment where the slip is unstable.

What are the surgery options for spondylolisthesis?

When spondylolisthesis needs surgery, the choice depends on the type of slip, its grade, whether it is stable, and whether it is pressing on nerves. The main options are:

1. Decompression

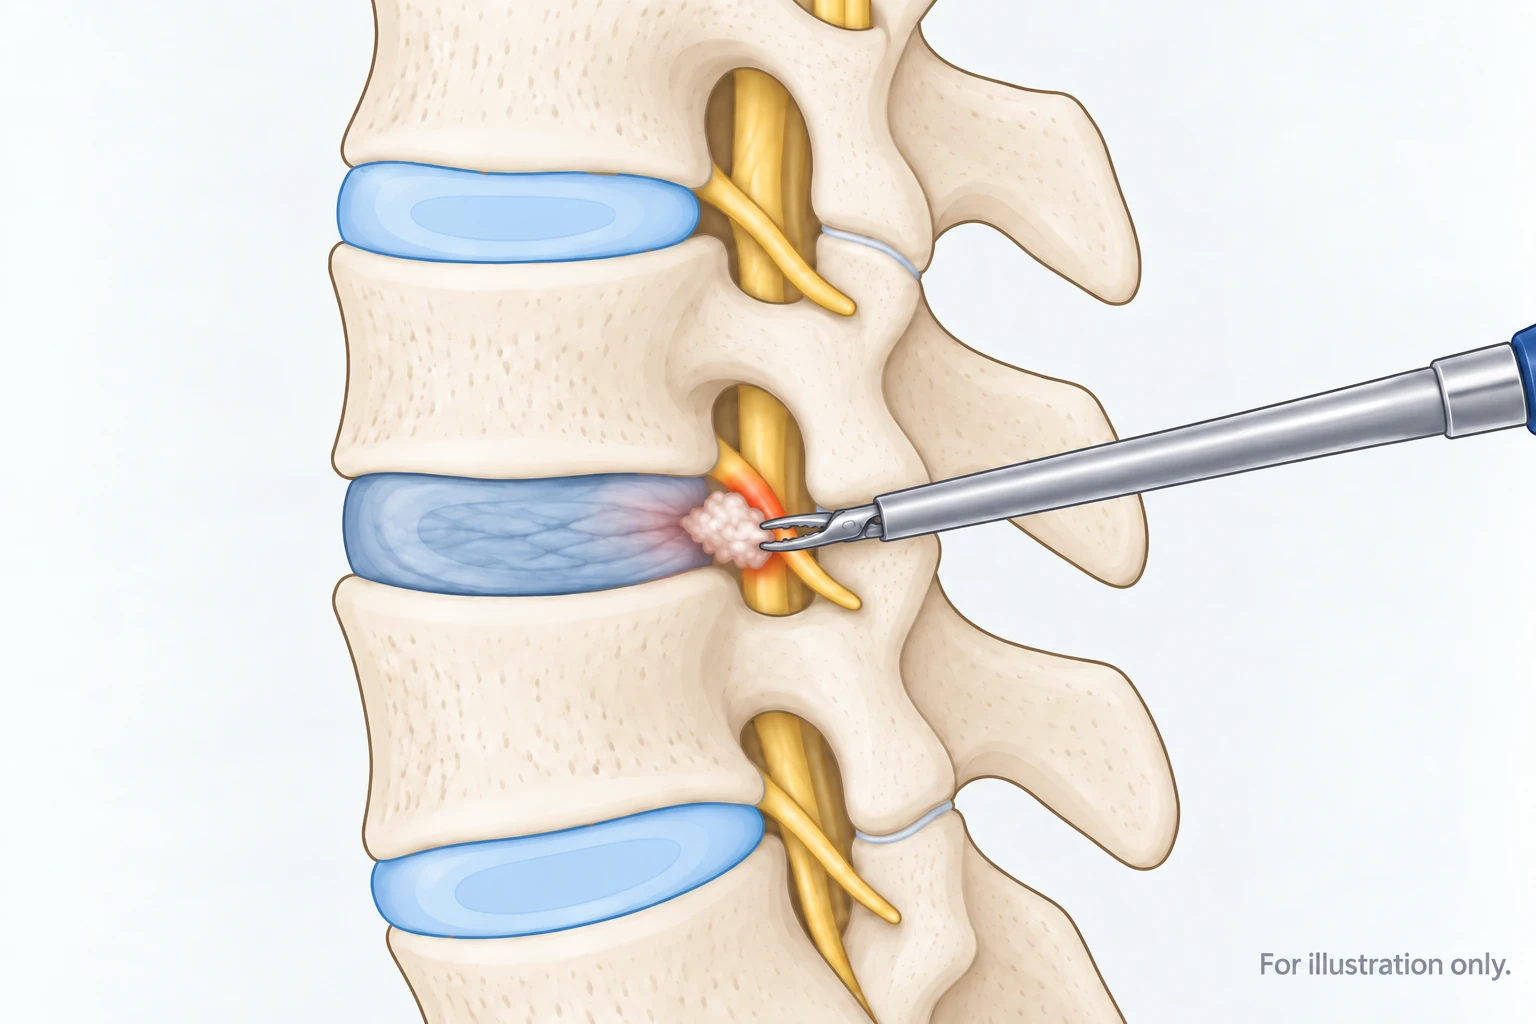
Where a stable, low-grade slip is pinching nerves, removing the bone and thickened ligament that are crowding them relieves the leg symptoms, and for these cases it can be enough on its own. Recent studies of degenerative spondylolisthesis have found that adding a fusion to the decompression often does not improve outcomes, so decompression alone is frequently reasonable and a fusion should not be automatic.

2. TOPS Facet Joint Replacement or Dynamic stabilisation (HPS 2.0)

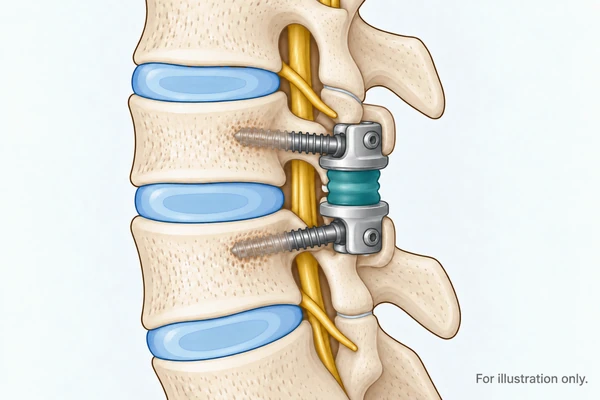
Where a low-grade degenerative slip needs support after the decompression, a TOPS Facet Joint Replacement can hold the level while keeping it moving, instead of fusing it. Our German specialists use the TOPS and the HPS 2.0 system, which is designed for exactly this setting: a degenerative slip up to grade 1, following decompression.

3. Minimally Invasive Fusion

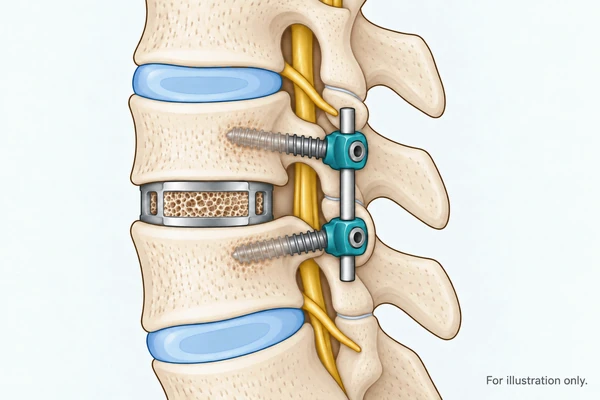
Where a slip is unstable, higher-grade, or part of a larger deformity, a fusion realigns the spine and locks the unstable segment, and here it is the right choice rather than something to avoid. It does not have to be a large open operation: approaches such as oblique lateral interbody fusion (OLIF) and anterior lumbar interbody fusion (ALIF) reach the spine through a small window at the side or front, sparing the back muscles, with less blood loss and a quicker recovery than traditional open fusion.

The aim is to match the operation to the slip, doing enough to free the nerves and stabilise the spine where it is genuinely unstable, without doing more than the problem calls for.

A patient's story: choosing a minimally invasive fusion

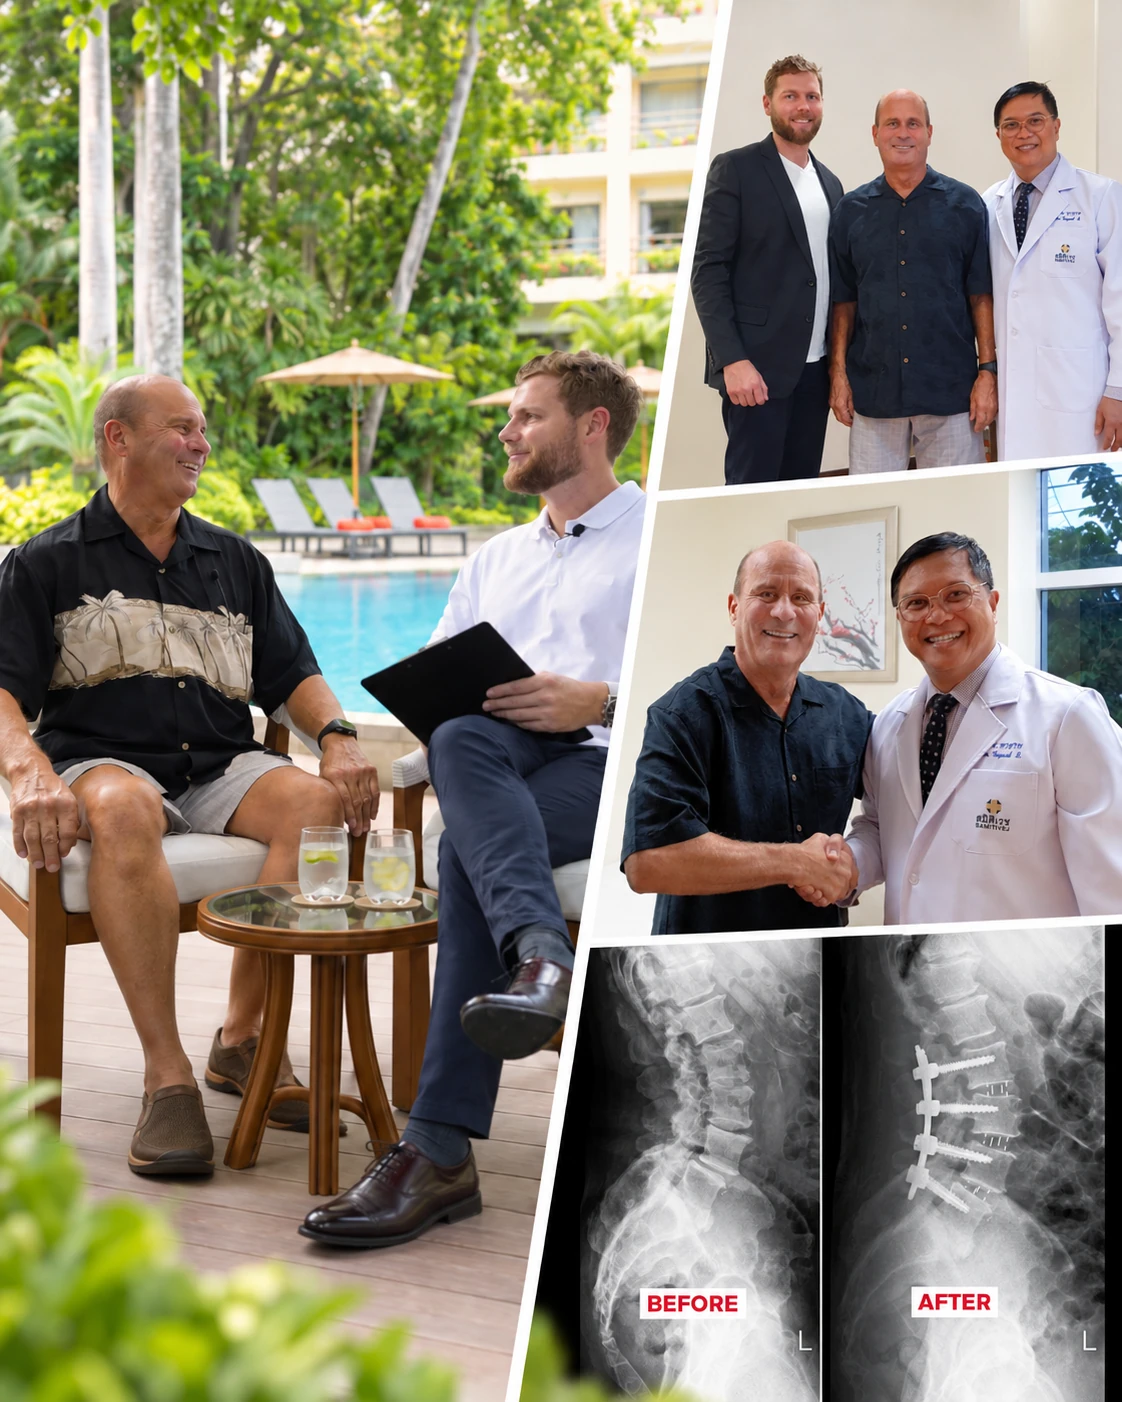
Steve, a healthy and active 64-year-old from Florida, had worked through physiotherapy, injections, and steadily dialling back his activities, but his lower back only got worse. He first looked into motion-preserving surgery in Germany, but his case did not suit it: alongside a vertebral slip he had advanced degeneration and scoliosis, and our specialists advised him honestly that a reconstructive fusion to realign the spine would give him the best result.

Rather than a large open operation, Steve chose a minimally invasive approach: an L2 to L5 oblique lateral interbody fusion (OLIF) with Dr. Tayard at a partner hospital in Bangkok. The technique reaches the spine through a small window at the side, without cutting through the back muscles. After the reconstruction he needed only four days in hospital before starting his rehabilitation.

What we see at Spine Connection

Spondylolisthesis covers a wide range, from a stable, low-grade slip that may never need surgery to an unstable one that does. Where a slip is stable and low-grade, we look first at whether decompression alone or a motion-preserving option fits. Where it is unstable or advanced, a fusion is the right choice, and the priority is to do it in the least invasive way that will hold.

Dr. Tayard Buranakarl is a senior spine surgeon at the Bangkok Spine Academy and Bangkok International Hospital, and a Key Opinion Leader for Medtronic. He trained internationally, including a fellowship at UCLA, and introduced several minimally invasive fusion techniques in Thailand, among them OLIF, which he uses to treat spondylolisthesis through a small side approach that spares the back muscles.

Frequently Asked Questions

Listhesis means a vertebra has slipped out of line with the one below it. Anterolisthesis means it has slipped forward, which is the common direction; retrolisthesis means backwards. Spondylolisthesis is the full term for the forward slip. Reports often add a grade from I to IV describing how far it has moved.

Grade 1 means the vertebra has slipped up to 25 percent of the way forward over the one below. It is by far the most common grade, and most degenerative slips stay there. Low-grade slips are usually stable and often managed without surgery. The grade guides treatment but does not predict pain, for example a grade 1 slip can be painful and a higher one can cause few symptoms.

The most common is lower back pain, often worse with standing, walking, or bending backwards, and easier with rest. Tight hamstrings are common. If the slip narrows the space around the nerves, it can also cause pain, numbness, tingling or weakness travelling into the buttock and leg, and in older adults the leg heaviness on walking that comes with spinal stenosis. Many people have a slip and no symptoms at all.

Positions and activities that arch the lower back backwards tend to aggravate it. This also includes standing for long periods, walking downhill, and extension-based exercise. Sports that repeatedly arch the back, such as gymnastics, cricket bowling and weightlifting, are also how the isthmic type often develops in the first place. Forward-leaning positions and sitting usually give relief.

It usually does not. But a slip that is significantly compressing the nerves at the base of the spine can, and that combination is a medical emergency. Loss of bladder or bowel control, numbness around the groin or inner thighs, or leg weakness that is quickly getting worse needs immediate care, not a wait-and-see approach. These symptoms are uncommon, but they should never be ignored.

A standing side-on X-ray shows the slip and is used to grade it on the Meyerding scale. X-rays taken bending forwards and backwards show whether the segment moves abnormally, which tells the surgeon whether the slip is stable or unstable, which is often the most important question. An MRI or CT then shows whether the slip is pressing on nerves. As always, imaging is read alongside symptoms.

No, and it should not be automatic. Where a stable, low-grade slip is pinching nerves, decompression alone frequently relieves the leg symptoms. Where the segment genuinely needs support, dynamic stabilisation such as the HPS 2.0 System can hold it while keeping it moving. Fusion is the right answer for an unstable or higher-grade slip, and even then it can often be done through minimally invasive, muscle-sparing approaches.

Been told you need a spinal fusion?

Been told you need a spinal fusion?

If you have been told you need a fusion for spondylolisthesis, or you are stuck on a waiting list, or facing a cost you cannot meet at home, it is worth a second opinion before you commit. Our specialists in Germany and Thailand can review your imaging and tell you honestly whether a stable, low-grade slip might be handled with a decompression or a motion-preserving option, or, where a fusion genuinely is needed, whether it can be done in a minimally invasive, muscle-sparing way.

Sources

  1. Spondylolisthesis. StatPearls (updated 2023). (Definition, Wiltse types, Meyerding grading, symptoms; most slips are low-grade.) (https://www.ncbi.nlm.nih.gov/books/NBK430767/)
  2. Surgical and non-surgical management of spondylolisthesis: a comprehensive review. 2024. (Isthmic and degenerative are the most frequent types; isthmic from a pars defect, often in young athletes; management overview.) (https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12022737/)
  3. Kaiser R, et al. Decompression alone versus decompression with instrumented fusion in the treatment of lumbar degenerative spondylolisthesis: a systematic review and meta-analysis of randomised trials. J Neurol Neurosurg Psychiatry, 2023. (Adding fusion to decompression did not improve outcomes for degenerative spondylolisthesis.) (https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10359551/)
  4. Management for degenerative lumbar spondylolisthesis: a network meta-analysis and systematic review based on randomized controlled trials. International Journal of Surgery, 2024. (https://www.ncbi.nlm.nih.gov/pmc/articles/PMC11093486/)
  5. Lumbar dynamic pedicle-based stabilization versus fusion in degenerative disease: a multicentre, double-blind, randomized controlled trial. J Neurosurg Spine, 2022. (Category-level reference for the dynamic-stabilisation approach; not a study of the HPS 2.0 device.) (https://thejns.org/spine/view/journals/j-neurosurg-spine/37/4/article-p515.xml)
We're here
to help.
Leave your details and we will contact you to answer your questions.

Get a Spine Specialist's Opinion for Your Spondylolisthesis

Leave your details and we will contact you to answer your questions. We're here to help.


    Join Our Youtube Channel

    Watch videos showcasing the latest technologies and surgery techniques, and keep up to date with patient stories from around the globe.